Your first step to recovery

What is your Rotator Cuff and What does it do?
 

You may have seen videos or posts online about people talking about a specific area of your shoulder known commonly as the “Rotator Cuff” and wondered what they were on about. Your shoulders do a lot of important things you might take for granted! They help you get something off a high shelf, comb your hair, or play a game of cricket.

It’s a complicated process that your body makes look easy. And your rotator cuff is a big part of that. It protects and stabilizes your shoulder joint and lets you move your arms over your head. It’s importance is widely used in sports like swimming, tennis and netball.

In New Zealand healthcare, shoulder injuries have one of the highest prevalence when it comes to ACC claims and overall cost. Within this, rotator cuff injuries are among the most common pathologies affecting New Zealanders. Other pathologies include acromioclavicular injuries, dislocations, osteoarthritis and frozen shoulder.


So, what exactly is the cuff and how does it influence the shoulder?

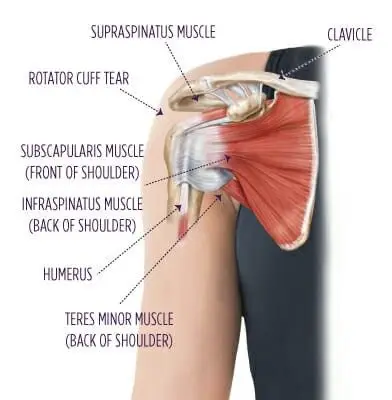
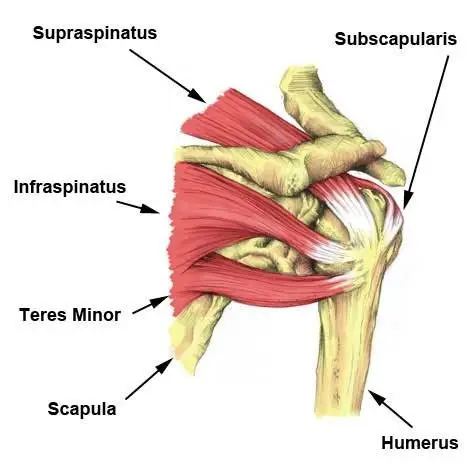
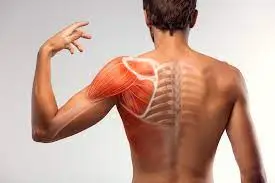
  • The rotator cuff (RC) is a combination of four muscles that run through and attach onto specific areas of the humeral head (top of the arm bone).

  • Supraspinatus, Infraspinatus, Teres minor and Subscapularis are the four muscles comprising the RC and each one plays an important role however they all contribute to shoulder stability:

Supraspinatus

Infraspinatus

Teres Minor

Subscapularis

A thin triangular muscle that helps perform abduction

A thicker, triangular muscle that performs external rotation.

The smallest muscle of the cuff, helps with rotation as well

The largest muscle of the cuff performs internal rotation (arm behind your back!)


Many people suffer from shoulder pain, so here are the most common injuries that can happen at the rotator cuff:

Rotator Cuff Tear:

A rotator cuff tear is often the result of high levels of load over a short amount of time or a high impact force stressing one or more of the tendons/muscles. Fortunately, majority of tears are partial. Tears are more common in people with jobs that involve heavy loading or lifting or in high impact sports like rugby. It also can happen suddenly if you fall on your arm or try to lift something heavy. Common and easily treatable with conservative management by a physiotherapist, a rotator cuff tear can come right.

Rotator Cuff Tendinopathy:

A rotator cuff tendinopathy is the most common shoulder pain complaint/injury resulting in inflammation and irritation of one or more of the cuff tendons. This pathology is more common in individuals who have an occupation where repetitive use of the shoulder, particularly in an overhead position such as carpenters or painters, or individuals that play highly repetitive, throwing sports like tennis, baseball or volleyball. Once again, this injury is treatable by a physiotherapist, conservative management can be very effective in treating these injuries with a thorough, well planned exercise program to help get patients back to doing what they love.

Majority of people experience pain around the shoulder joint, with some movements being highly provocative. Tenderness on touch at the affected site is also common – this helps your physiotherapist hone in on potentially which tendon is causing those problems!


Medical management vs Physio management

 

Medical management will be advised by your local GP if you decide to see them first. They might prescribe NSAIDs (anti-inflammatory medications such as ibuprofen) to help with the pain you’re experiencing and recommend you see a physiotherapist. Depending on your injury as well as your ability to function, surgery may be an option if conservative medical and physio treatments don’t help. Most people get by without the need of surgery but some tears can be too large to heal without the use of surgical intervention.

Physiotherapy management is designed around reducing pain and disability, restoring range of motion and helping people return to work or sports to perform how they were prior to the injury. In the early stages of these injuries, rest and ice and/or heat are recommended to allow the inflammation to settle – then your physiotherapist will begin to introduce a detailed exercise program, this may include:

  • Isometric (static hold) exercises
  • Resisted movements using bands
  • Range of motion exercises to restore lost movement
  • Functional loading – task specific or sport specific

If this is successful, the last step is to build back up the strength that was lost over time – this is done by concentrically (against gravity) loading the affected tendons/muscles in a way that they adapt and lay down more tissue, grow and becoming stronger in hopes that you get to return to what you enjoy!

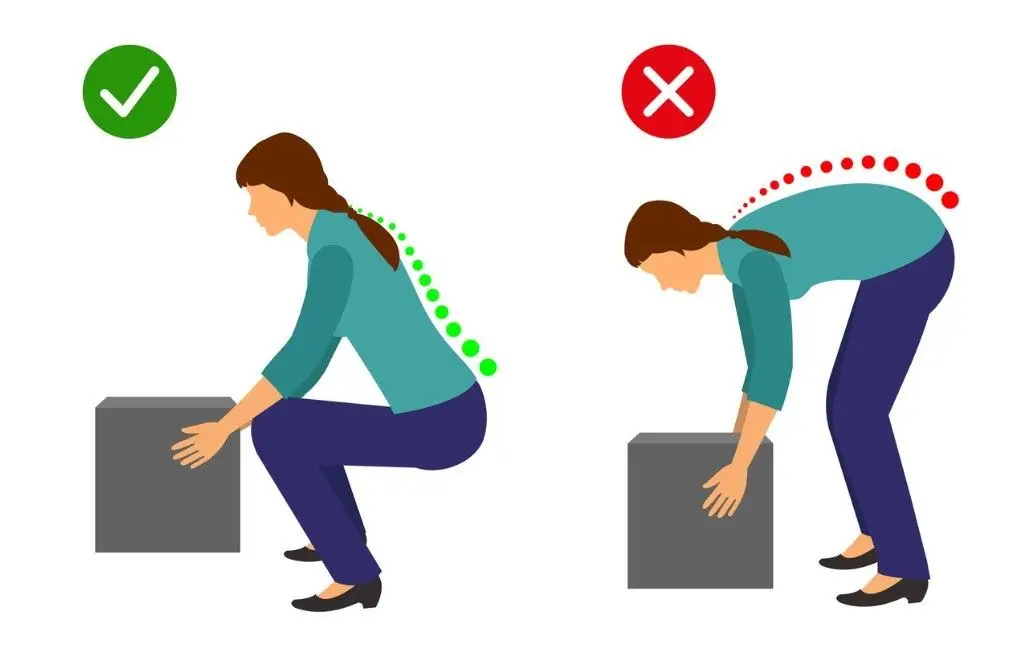


Lifting Mechanics

IS IT DANGEROUS TO LIFT WITH A BENT BACK?

One common belief about lifting is that rounding your back when lifting an object is considered dangerous while lifting with a straight back is considered safe…


However, there is a lot of misinformation circulating around lifting mechanics and what is deemed “good technique” versus “bad technique.”

Here are some key myths and misinformation that you may have heard:


A ROUNDED BACK WHILE LIFTING OVER STRESSES THE BACK MUSCLES AND LIGAMENTS

  • Research has shown that regardless of lifting position, whether you’re stooped, squatting or weightlifting, your back has to produce the same amount of force. Statistically speaking, it’s not significantly different.


FLEXING THE SPINE WHILE LIFTING INCREASES THE LOAD ON THE LUMBAR DISCS

  • Under heavy loads, discs are unlikely to fail unless >95% flexion is achieved (which is near impossible)

  • With low loads, the disc is unlikely to fail unless you do thousands of repetitions continuously

  • Your body is an amazing adapter, this includes discs! Your discs can adapt and become more and more able to handle loads when stressed appropriately


THESE COMPOUND TO CAUSE INJURIES AND PAIN TO THE BACK MUSCLES AND DISCS

  • Resistance training has demonstrated through countless studies the ability to increase bone mineral density (BMD) of the lumbar spine. BMD is actually positively associated with the strength of the spinal discs and ligaments at that level. With appropriate loading and training, disc, ligament, bone and muscles are going to adapt favourably


A NEUTRAL SPINE IS SAFER, STRONGER, MORE EFFICIENT AND BETTER TO LIFT WITH

  • There is no significant difference between activities that encourage more spinal flexion and one’s that do not in the long term

  • Lifting with lumbar flexion is not a risk factor for low back pain

  • Research has shown lifting with a bent back is more metabolically and neuromuscularly efficient

  • When the spine is in extension during bent over activities, the hip is actually flexed to a greater degree – decreasing the ability for the glutes and hamstrings to create as much internal torque. Flexing the spine reduces this effect and reduces the moment arm for the hip extensors


STOP BACK PAIN & INJURIES BY LIFTING WITH A NEUTRAL SPINE

  • Your lumbar spine flexes every time your hip flexes! It is impossible to isolate one versus the other. It is also impossible to not flex while doing common movements

  • Extreme flexion however (>/=100%), may pose an increased risk under heavy loads, but not at light loads


You may still be wondering why you have back pain (stay tuned for our next blog!). Your pain may not be directly related to your lifting strategy.


Could you have pain with forward bending? Absolutely.

Is bending at the lumbar spine an increased risk for pain or injury? In the vast majority of situations, no.

If I have pain with forward bending, is it bad to temporarily limit doing so? Not at all.

Should I fear bending at the spine with or without pain or injury? No. Being fearful of flexing/moving your spine is actually a stronger predictor of disability and back pain.


Work on moving through your spine, after all it’s what it is designed to do! Choose comfortable movements and gain confidence over time, then build up your strength gradually with resistance training – try and not to push too fast, we want nice, healthy adaptation! Give your body time to adapt, back pain is not quick fix sometimes but you are resilient and with healthy, normal movements and some patience, you will be okay.

Disorders of the Achilles Tendon

Basic Anatomy

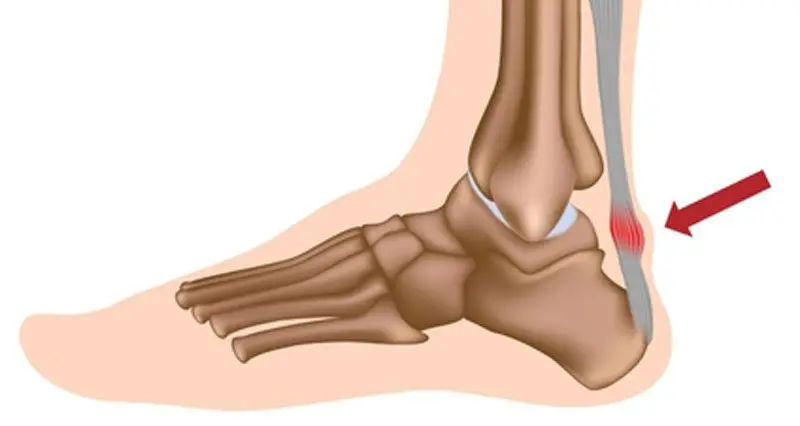
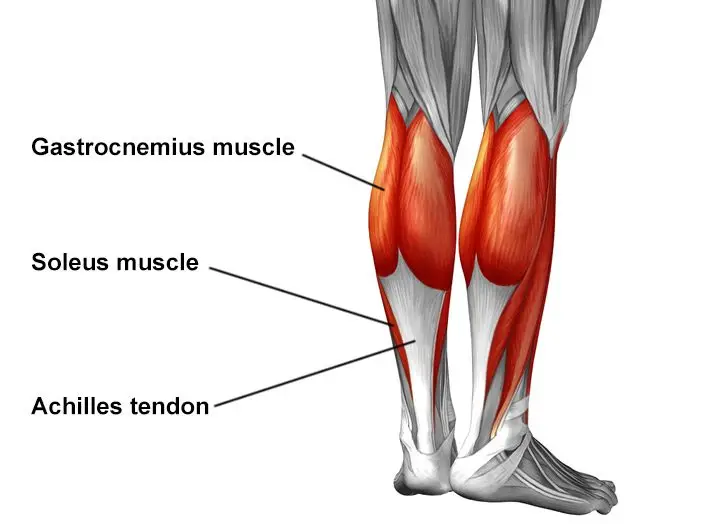
The Achilles tendon is the largest tendon in the human-body. It is a band of tissue that connects your calf muscles to your heel bone (calcaneus). This tendon primarily facilitates general mobility such as walking, running, climbing stairs, jumping, and standing on your tip toes, by helping to raise the heel off the ground.


Common Achilles Pathology

Achilles tendinitis and tendinosis are two common disorders and are typically classified as overuse injuries.

Achilles tendonitis involves inflammation of the Achilles tendon. Inflammation is the body’s natural response to injury or disease, and often causes swelling, pain, or irritation. This inflammation is typically short-lived. Over time, if this is left resolved, the condition may progress to degeneration of the tendon- Achilles tendinosis, in which case, the tendon loses its organized structure and is likely to develop microscopic tears.

There are two types of Achilles tendonitis and it is based on which part of the tendon is inflamed:

  • Insertional Achilles tendonitis affects the lower portion of your tendon where it attaches to your heel bone.
  • Non-insertional Achilles tendonitis involves fibres in the middle portion of the tendon and tends to affect younger people who are active.

In both non-insertional and insertional Achilles tendinitis, damaged tendon fibres may also calcify (harden) and often bone spurs (extra bone growth) develop with insertional Achilles tendinitis. Achilles tendonitis may also increase your risk of sustaining an Achilles tendon rupture (tear).

Causes

Typically referred to as “overuse” conditions, Achilles tendonitis and tendinosis are often caused by the sudden increase in repetitive activity involving the Achilles tendon. This can put too much stress on the tendon too quickly, that can then lead to micro-injury of the tendon fibres. Because of this ongoing stress on the Achilles, the body is not able to repair the injured tissue. The structure of this tendon is then modified, resulting in continued pain and other symptoms. The Achilles tendon also has poor blood supply that makes it more susceptible to injury and may make recovery from injury slow.

Common factors that may lead to the development of disorders of the Achilles tendon include:

  • Weak and/or tight calf muscles
  • Rapidly increasing the amount or intensity of exercise within a short span of time
  • Hill climbing or stair climbing exercises
  • Presence of bony spurs in the back of your heel
  • Changes in footwear – especially changing from wearing high-heeled shoes to flat shoes
  • Wearing poor fitting, inappropriate, or worn out shoes during sporting activities
  • Exercising without adequate warm-ups and stretching
  • A sudden sharp movement which causes the calf muscles to contract and the stress on the Achilles tendon to be increased. This can cause the tendon fibres to tear.
  • Excessive mobility
  • Poor feet positioning and biomechanics (excessive pronation and flattening of the arches of the foot)


Symptoms

Achilles tendon pain: Causes. when to see a doctor, and treatment


Common symptoms include:

  • Pain and stiffness along the Achilles tendon especially first thing in the morning
  • Pain along the tendon or back of the heel that worsens with activity
  • Severe pain the day after exercising
  • Visible thickening of the tendon
  • Tenderness to touch
  • Bone spur
  • Swelling that is present all the time and gets worse throughout the day with activity

If you have experienced a sudden “pop” in the back of your calf or heel, you may have torn your Achilles tendon. Please seek urgent medical attention if you think you may have torn your tendon.

Diagnosis

If Achilles tendonitis or tendinosis is suspected, please deter from any activity or exercise which causes the pain. It is advisable to see your doctor or physiotherapist as soon as possible so that an accurate diagnosis may be made and appropriate treatment recommended.

You will be asked about the nature and duration of your symptoms and the medical professional assessing you will have a look at your foot and ankle. Ultrasound scanning may be used to evaluate the damage to the tendon and/or surrounding structures.

An MRI may be recommended if symptoms persist. X-rays may also be taken to rule out other disorders which may cause symptoms like Achilles tendonitis and tendinosis.

Achilles Tendonitis - Ankle - Conditions - Musculoskeletal - What We Treat  - Physio.co.ukHow to Treat Achilles Tendinopathy with Physical Therapy -  prohealthcareproducts.com

Treatment

Treatment will depend on the nature, severity, and length of the injury. Generally speaking, the longer the symptoms are present before treatment commences, the longer the timeframe until full recovery is attained.  Full recovery may take between three and nine months.

Initial treatment options in the early stages may include:

  • Rest – to avoid further injury to the area
  • Ice – to reduce inflammation
  • Elevation – to reduce swelling
  • Non-steroidal anti-inflammatory drugs to reduce pain and inflammation.

 How physiotherapy can help:

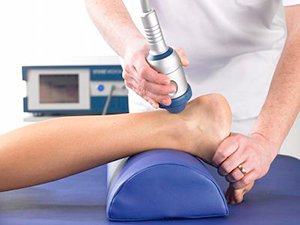
Physiotherapy typically focuses on two main areas: treatment and rehabilitation. Treatment may entail massage, shockwave therapy, acupuncture, gait re-education, and gentle stretching, whereas, rehabilitation predominantly entails strengthening of the Achilles and surrounding musculature.

Strengthening of the muscles surrounding the Achilles tendon facilitates healing in the tendon itself. Strengthening is attained through the utilization of specific exercises, that will be taught by your physiotherapist. It is common for the rehabilitation programme to take up to three months.


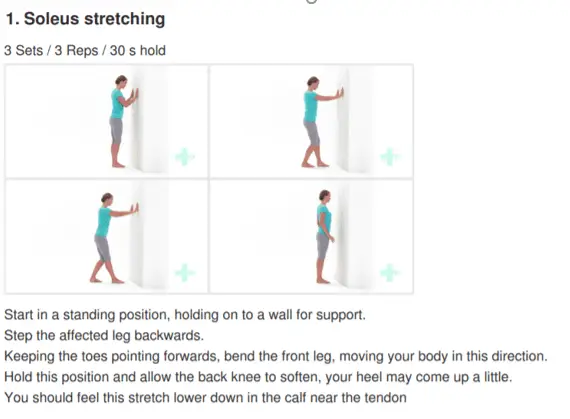
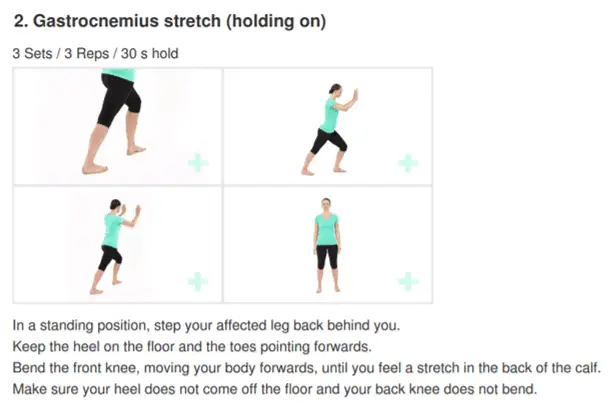
Exercises


KNEE PAIN

Knee pain is one of the most common musculoskeletal complaints that affects peoples of all ages.
Knee pain can result from injuries of traumatic nature or due to complications from medical conditions.

Depending on the structures involved, pain can be localized to a specific area or be felt all
around the knee.


ANATOMY OF KNEE

The knee joint is a hinge joint. Other than bearing the weight of the body, it’s primary function is to bend, straighten and rotate to a small degree. To achieve this function, the knee joint relies on a number of structures.


Image result for knee anatomyImage result for knee anatomy


Bones

Knee joint consists of four bones to provide structure and weight-bearing ability.

  •  Lower end of thigh bone (femur)
  •  Upper part of shin bone (tibia)
  • Knee cap (patella)
  • Fibula (not involved in weight-bearing, but provides attachments for ligaments and tendons)


Ligaments

Four important ligaments connect the two big bones, providing multi-directional stability.

  • Cruciate ligaments

Anterior cruciate ligament (ACL)

Posterior cruciate ligament (PCL)

  • Collateral ligaments

Medial collateral ligament (MCL)

Lateral collateral ligament (LCL)


Cartilage

  • Glossy cartilage lines the end of each bone to protect and allow smooth movements against each other with almost no friction.
  • Meniscus is another type of strong cartilage that lines the upper surface of the tibia bone to cushion and stabilize the knee.


Tendons

There are two important tendons located on the front of the knee joint.

  • Quadriceps tendon is a strong durable tissue that extends from the quadriceps muscle and connects it to the knee cap.
  • Patella tendon connects the knee cap to the tibia bone.


Bursa

Bursa are fluid filled sacs that are found in areas that require the most protection. They occur where ligaments, muscles, skins, tendons or bones rub together.


Muscles

Many muscles cross the knee joint, some of which cross from the hip or ankle joints. Due to this, some people may experience knee pain as a result of muscle imbalances such as weakness, poor flexibility and or dynamic control.


CAUSE OF PAIN

Some of the common causes of knee pain include:

  • Ligamentous sprain
  • Meniscus injuries (bulge or tears)
  • Fracture or dislocation
  • Tendinitis, Sprains
  • Bursitis
  • Calcification
  • Baker’s cyst
  • Arthritis (osteoarthritis)
  • Overuse syndromes (patella-femoral syndrome, chondromalacia)
  • Autoimmune conditions (Infection, Gout, Lupus, rheumatoid arthritis)


WHEN TO SEEK HELP

Consult your doctor or physiotherapist if your symptoms have not subsided after one-week of consistent self-management (RICE, pain medications or alternative pain-relieving modalities), or if your knee pain is stopping you from managing your hobbies or day to day activities.


Immediate medical attention: 

Knee pain from with the following signs and symptoms may require immediate attention:

  • Severe pain
  • Pain that does not resolve with rest
  • Sudden swelling or bruising
  • Clicking or locking of the knee
  • Inability to bend or straighten the knee
  • Inability to weight bear


SIGNS AND SYMPTOMS

  • Pain
  • Swelling
  • Bruising
  • Stiffness
  • Clicking, locking
  • Redness


DIAGNOSIS:

Treatment of your knee pain will depend on its underlying cause. So, it is all about the diagnosis.

A focused subjective and physical examination of your knee will be performed by your physiotherapist.


Subjective

Your physiotherapist will ask a range of questions

  • Location of pain – front or behind the knee
  • Description of pain – dull ache or sharp
  • The behavior of pain – constant or intermittent
  • Aggravating and easing factors
  • General health
  • Goals of treatment


Physical assessment

Your physiotherapist will inspect your knee joint to diagnose the source and the potential underlying cause(s) of pain.

You may be referred to have radiological Imaging to make or confirm the diagnosis.


Radiology

Image result for xray knee


TREATMENT

In most cases, individuals suffering from knee pain respond well to conservative modes of treatment (pain relief, physiotherapy, acupuncture, etc). Surgical intervention may be required where conservative management has failed to optimize function and reduce pain.


CONSERVATIVE MANAGEMENT

A self-management remedy to control inflammation (pain and swelling) in acute or chronic knee pain is using the ‘RICE’ principle (rest, ice, compress, elevate)

  • Rest – refrain from activities that impose repetitive strain or aggravation of knee pain
  • Ice – use an ice pack for 10-15 minutes, 2 to 3 times per day (with care)
  • Compress – use a compression bandage to reduce swelling (not to be worn when sleeping)
  • Elevate – using pillows elevate injured leg. This works best when the leg is higher than the level of heart, to use gravity to help facilitate the circulation of fluid.


Pain medications

Over the counter pain relievers such as non-steroidal anti-inflammatory medications (ibuprofen, celecoxib) play an important role in reducing inflammation and pain.

(Note: If you have problems with bleeding, stomach ulcers or other liver, kidney conditions, anti-inflammatory medications MUST NOT be consumed without consulting your doctor. 

Visit your general practitioner for more information on what medications are right for you.


Physiotherapy

After establishing your diagnostic findings, your physiotherapist will devise a tailored recovery programme to help you manage your pain, improve strength and flexibility.

Your physiotherapist will work with you to advance your understanding of your symptoms and provide a range of exercises, stretches and self-managing strategies that will help you be in control of your recovery.

As required, your therapist may liaise with your doctor or other health professionals (acupuncturist, podiatrist, knee specialists) to facilitate your progress.


Acupuncture/Acupressure

Acupuncture and acupressure are two different options available for individuals suffering from pain and swelling. While both aim to help control inflammation and fasten healing and recovery, acupuncture involves inserting thin needles into the body, whereas acupressure relies on hand pressure and some forms of massage.


Steroid Injection

In some instances, knee injections are recommended by your physiotherapist or doctor to reduce inflammation and relieve pain.


SURGERY

Surgical intervention may be required where conservative management has failed to optimize function and reduce pain. In this case your physiotherapist will refer you to a surgeon for the opinion of care.


EXERCISES FOR KNEE PAIN

The thought of exercise when you have knee pain can be daunting. However, your trusted physiotherapist will work with you to provide specific ‘pain-free’ exercises to get you started on effective strengthening.

Image result for knee exercise cycling

Alternatively, low-impact activities such as cycling or elliptical machines are great. Notice what feels right for you. Swimming, jogging in water, or water aerobics may be appropriate if skin integrity is maintained.

Note: muscle soreness after a hard workout is normal. 

If you experience sharp, shooting, or sudden knee pain you must consult your physiotherapist or doctor.

5 COMMON MISCONCEPTIONS ABOUT PHYSIOTHERAPISTS – PART 2

Myth 1: When you see a physiotherapist you just lie on the bed and get given an ice or heat pack.

At Physio Fusion we use an active approach to treatments. Physiotherapy will include manual hands-on therapy to facilitate tissue healing and tissue load tolerance alongside an exercise program individualized to your needs.

Myth 2: If I have elbow pain then the injury must be in my elbow.

The area of pain is not always the area that is the issue! It may be a result of a previous injury that was never fully rehabilitated. This is where we can help you out. Our assessment will consist of gathering information on your presenting complaint, any previous injuries or traumas (physical and emotional) and a medical history followed by an objective evaluation of your body. This allows us to get to the root cause of the pain and manage your symptoms most effectively.

Myth 3: I can’t do any of my normal activities while I attend physiotherapy.

Not true! Our Physiotherapists want to keep you as functional as possible whilst allowing your injury to heal. During the initial assessment your physiotherapist will determine what activities you can do and advise you on those that must be avoided. You will then be given clear and timely objectives to ensure you reach your goals to get you back doing what you love!

Myth 4: A scan will show me exactly what is wrong.

Sometimes it will, but sometimes it won’t. It’s no secret that our bodies change as we age, so even people without pain are likely to have an imperfect scan. Medical imaging can sometimes play an important role in the assessment and management of your musculoskeletal issue. When necessary, your physiotherapist will know what type of imaging to refer you for.

Myth 5: Is cracking my back/neck/knuckles bad for me?

There is no strong evidence to suggest that ‘cracking’ your joints causes degeneration, laxity or instability. The ‘cracking’ occurs when we move a joint to its end range. The audible sound happens because of ‘cavitation’ in the joint; this involves gas bubbles popping within the fluid surrounding the joint as pressures change.

But is it good to crack?

Self manipulation can be a helpful way to reduce the feeling of stiffness or tightness. If you are finding that you need to ‘crack your joints’ often it is good to know that there are many other more beneficial ways to provide greater long term relief.

Top tips:

  1. Ask your physiotherapist to provide you with some specific exercises to help you overcome the feeling of stiffness or tightness.
  2. Move regularly and avoid movements or positions that exacerbate your symptoms until you have been seen by your physiotherapist.

Rotator Cuff Injury

Rotator cuff injuries are the most common source of shoulder problems. They can range from minor sprains causing impingement type symptoms, to massive tears resulting in severe loss of function and pain. They commonly occur as a result of acute injuries (sports, falls), chronic overuse (repetitive loading) or due to gradual aging.


Anatomy of shoulder

The shoulder joint (glenohumeral joint) is the most mobile joint in the human body. It comprises of the humeral head (top portion of upper arm bone) which fits in the glenoid cavity of the scapula (shoulder blade) to create a ball and socket configuration. This anatomical configuration results in limited bony contact between the humeral head and the glenoid fossa, which reduces the stability of the joint.

Several passive and active structures stabilize and maintain proper biomechanics of the shoulder joint.

  • Passive stabilizers include the ligaments, joint capsule, cartilage and the bony concavity of glenoid fossa. Thick cartilage known as labrum lines the glenoid fossa to further deepen the groove by about 50% which is advantageous in stabilizing the shoulder joint during the articulation.
  • Dynamic stabilizers of the glenohumeral joint is gained from the coordination of rotator cuff muscles that compress the passive structures providing stability and mobility as whole.

The four rotator cuff muscles include:

  • supraspinatus
  • infraspinatus
  • subscapularis
  • teres minor
 

Injury to any or all these four muscles, including the tendons that attach the muscles to bone can result movement dysfunction and severe pain.

Other important joints of the shoulder complex include:

  • sternoclavicular joint
  • arcomioclavicular joint
  • scapulothoracic joints
 

Types of rotator cuff pathology

Acute rotator cuff tear

Acute tears result from sudden forceful lifting of the arm against resistance or in an attempt to cushion a fall (for example, heavy lifting or a fall on the shoulder).

Chronic rotator cuff injury

Chronic rotator cuff tears are the result of gradual wear and tear that occurs slowly overtime with pain persisting more than three months. 

There are several factors that contribute to this which include: repetitive strains, bone spurs, poor healing rate due to age.

Tendinitis and Tendinosis

More often than not the term tendinitis and tendinosis are interchangeably used to describe a similar tendon pathology. However, the factor that differentiates the two is the time of injury (acute or chronic).

Tendinitis results from acute injury to the tendon which sets off an inflammatory process characterized by pain, swelling, and redness. On the other hand, tendinosis is a chronic pathology that does not involve an inflammatory process. It is characterized by degeneration of collagen fibers in response to persistent micro-trauma, vascular compromise and aging.

Signs and symptoms

Symptoms of a rotator cuff injury are due to the inflammation that accompanies the strain. Swelling that forms within the small space of the joint prevents the normal mechanics of the shoulder, resulting in the clinical picture of pain and decreased range of motion.

  • Acute rotator cuff tears

    Tearing sensation
    Immediate severe localised pain
    Reduced strength
    Symptomatic clicking
    Reduced and worsening pain with movements
    Affects daily activities (personal care, lifting, reaching etc)

  • Chronic rotator cuff tears

    Generalized deep dull ache, sharp onset of pain with movements
    Global shoulder weakness
    Reduced movements and daily activities (especially moving to the side, reaching behind back)

When to seek medical treatment

See your doctor or a physiotherapist if you experience any of the following symptoms in the shoulder:

  • Pain, especially pain that does not improve with rest
  • Swelling, redness or tenderness around the joint
  • Shoulder weakness
  • Reduced shoulder movement

Seek immediate medical attention if you experience the following symptoms:

  • Sudden, severe pain
  • Visible joint deformity
  • Inability to move or use your shoulder joint
  • Sudden swelling, discoloration
 

Diagnosis

To diagnoses an injured rotator cuff, your physiotherapist will begin with a thorough subjective and physical examination of your shoulder.

Subjective assessment

Your physiotherapist will begin with a thorough subjective assessment inquiring about your signs and symptoms of an acute injury as well as any symptoms that may suggest a more long-term problem.

Physical assessment

The physical examination often involves observation to look for muscle wasting, deformities, and/or changes in appearance of the injured shoulder to the unaffected side. Your physiotherapist will also palpate different areas of the shoulder complex to find the area of pain or tenderness. Further examination will involve assessment of movement and strength to establish injury to muscles or tendons.

Radiology

In addition, your physiotherapist may refer you for imaging tests to diagnosis the cause of your symptoms:

  • Ultrasound: examines soft-tissue structures (muscles, tendons, bursa)
  • X-rays: examines bone health, calcification
  • MRI: provides detailed imaging of areas injured (referred by doctors, specialists or surgeons)


Treatment

Early diagnosis and treatment of a rotator cuff tear may prevent symptoms such as loss of strength and loss of motion from setting in.

Initial treatment of rotator cuff tendinitis involves managing pain and swelling to promote healing. This can be done by:

  • avoiding activities that cause pain
  • applying cold packs to your shoulder three to four times per day
  • taking anti-inflammatory medications like ibuprofen and naproxen

Rehabilitation plays a critical role in both the nonsurgical and surgical treatment of a rotator cuff tear.

When a tear occurs, there is frequently atrophy of the muscles around the arm and loss of motion of the shoulder. An individualized physiotherapy program is necessary to regain strength and improve function in the shoulder.

Physiotherapy

Physiotherapy will initially consist of passive exercises to help restore range of motion and ease pain.

Once the pain is under control, your physiotherapist will prescribe exercises to help regain strength in your arm and shoulder.

Steroid injection

If you have persisting symptoms, your physiotherapist may recommend a steroid injection. This is injected into the tendon to reduce inflammation, which reduces pain.

Surgery

Surgery is recommended if you have persistent pain or weakness in your shoulder that does not improve with nonsurgical treatment. In which case, your physiotherapist will refer you to surgeon for an opinion of surgical intervention.


Exercises

Remember to consult your physiotherapist for precautions before starting or when progressing the exercises.

Range of movement exercise

  • Pendulums


  1. Lean forward with one arm hanging freely. Use your unaffected arm to brace against a chair for support.
  2. With your affected side, gently swing the hanging arm from side to side, forward and back, and in a circular motion for 15-20 seconds each direction.
  3. Slowly return to a standing position.
  4. Repeat 4-5 times a day
 
  • Shoulder pulley (Flexion)

 
  1. Put a chair against the door and sit so you are facing away from the door.
  2. Grasp the door pulley handles with both hands.
  3. Pull down on the pulley with your unaffected arm. This will lift your injured arm up over your head. Pull it as high as you can.
  4. DO NOT FORCE THE MOVEMENT. Your affected arm should be relaxed. The unaffected arm does the work.
  5. Hold for 5 seconds. Relax and repeat 10-15 times, 3 sets. Three times a day.

  • Shoulder pulley (Abduction)

 
  1. Put a chair against the door and sit so you are facing away from the door.
  2. Using door pulleys slowly pull down with your unaffected arm so that your affected arm raises up and to the side without effort.
  3. Your affected arm should be relaxed. The unaffected arm does the work.
  4. Hold for 5 seconds. Relax and repeat 10-15 times, 3 sets. Three times a day


  • Wand flexion

 
  1. Stand upright and hold a stick in both hands
  2. Cup the top end of stick with affected hand
  3. Using your unaffected arm hold the stick midway and drive the affected arm forward and up.
  4. Ensure your elbow is straight throughout
  5. Hold for 5 seconds and return to the starting position. Repeat 10 times.


  • Wand Abduction

 
  1. Stand upright and hold a stick in both hands
  2. Cup the top end of stick with affected hand
  3. Using your unaffected arm hold the stick midway and drive the affected to the side as high as able.
  4. Ensure your elbow is straight throughout.
  5. Hold for 5 seconds and return to the starting position. Repeat 10 times.


Strengthening exercises with band

  • Flexion

 
  1. Stand on one end of the band while holding the other end with your affected side.
  2. Whilst keeping your elbow straight, lift the band up to 90 degrees to shoulder level.
  3. Hold at the top for 1-2 seconds then lower slowly to starting position.
  4. Repeat 10-15 repetitions, rest 20-25 seconds, complete 3 sets.


  • Abduction

 
  1. Stand on the band while holding the band with affected hand.
  2. Keep your elbow straight, lift the band up to 90 degrees to shoulder level.
  3. Hold at the top for 1-2 seconds then lower slowly to starting position.
  4. Repeat 10-15 repetitions, rest 20-25 seconds, complete 3 sets.


  • External Rotation

 
  1. Attach the resistance band to a secure anchor at belly button height.
  2. Stand with unaffected arm perpendicular to the anchor.
  3. Place a towel between your elbow and your torso to stabilize your elbow
  4. Grab the band using your affected side and then slow pull the band away from your body by squeezing your shoulder blade in towards the middle of your back.
  5. Slowly return to starting position.
  6. Repeat 10-15 repetitions, rest 20-25 seconds, complete 3 sets.


  • Internal Rotation

 
  1. Attach the resistance band to a secure anchor at belly button height.
  2. Stand with affected arm perpendicular to the anchor.
  3. Place a towel between your elbow and your torso to stabilize your elbow
  4. Grab the band using your affected side and then slow pull in to your body
  5. Slowly return to starting position.
  6. Repeat 10-15 repetitions, rest 20-25 seconds, complete 3 sets.

Do you suffer from headaches, neck pain or back pain after sitting at your desk?

If your answer is YES, then be assured that you are not alone.

The fact is that with today’s technological advances most of us spend anywhere from 6 to 8 hours a day sitting at our desks working on a computer, laptop or mobile devices whether this is part of your work, study or simply spending leisure time.

Sitting for long hours at a time makes it extremely difficult to maintain proper posture. That’s because we are not made to for it, so many of us have the tendency lean forward, slouch our shoulders and hunch our backs. The unfortunate consequence of restoring to this kind of improper posture is the increase in unnecessary stress on multiple areas in your body including the neck, shoulders, back and arms resulting in pain and discomfort.

Adapting to poor posture on a repeated basis can affect your health and overall performance.

What are the effects of poor posture?

  • Poor Joint Alignment
  • Increased muscle tension
  • Increase joint compression
  • Reduced blood flow
  • Reduced lung expansion resulting in poor oxygenation
  • Fatigue
  • Reduce performance

How to fix it?

Fortunately headaches, neck pain or back pain caused by poor posture can be fixed with the following preventative measures:

1. Ergonomics

You may have heard of the term, ergonomics. To put it simply, ergonomics is a scientific discipline that aims to create sustainable workspace or environment to optimise productivity while maintaining health and safety standards.

Creating a sustainable work space environment begins with personalizing the setup of your desk, chair and equipment. Here are a few tips to keep in mind. 

Ergonomic Chair Setup: Sitting 

Adjust your chair
 There is no one-size fits all, so it is important to make your chair ergonomically fit for you.

  • Balanced posture. Sit well back into the chair with an upright and balanced posture.
  • Neutral spine. Slightly tilt the backrest forward to rotate pelvis so spine is in neutral position. You may intermittently recline back ever so slightly to offload your back.  
  • Hips high, feet flat. Adjust height of your chair so your hips are slightly higher than your knees, feet are resting flat on floor and at hip width apart. You may use a foot stool as an alternative if necessary.
  • Sit close. Scoot your chair close to the desk with little space left between the desk and your stomach

Ergonomic Desk Setup: Sitting 

  • Arms reach. Organise your frequently used stationary so that they are arms reach away.
  • Keyboard. Position keyboard directly in front of your body.
  • Elbows off. Keep elbows close to your body resting on the hand rests but off the desk. Only the muscular aspect of your forearm makes contact with the desk.
  • Stable neck. Setup your desk so as to limit excessive head movements.
  • Main monitor. Working with two monitors can be tricky, so use one as the primary monitor. Ensure monitor is centered and positioned at arms length. Height of the monitor should be adjusted so the top one third of the screen aligns with your line of vision

Ergonomic Desk Setup: Standing 

  • Posture.

    Stand tall, balanced and with your shoulder relaxed. Position your feet hip width apart for a strong base of support to anchor the weight of your upper body. Ensure you do not hyper-extend at your knees.
  • Elbow height.

    How to use a standing deskElevate your standing desk to your elbow height.
    Bend your elbows to 90 degrees. Ensure elbows remain off the desk, only the muscular aspect of your forearm makes contact with the desk.


2. Time for a Micro-breaks

No matter how ergonomically perfect your desk set-up may be it is important to take micro-breaks frequently.

There is mounting research that has found that taking frequent, short micro-breaks can be just as taking long breaks, if not more beneficial.

So do not be afraid to stand, walk or stretch for 1-2 minutes every 30 minutes.

3. Desk stretches

Keep yourself flexible with the following stretches.

Cross body stretch

Stand upright and prepare to start the shoulder stretch exercise.
This exercise stretches the muscles in your upper arm, upper back and shoulder and can be performed either sitting or standing.
Move your arm across your chest at the height of your shoulder.
Use your other hand to gently hold your elbow and pull the arm a little further across.
You should feel the stretch across the back of your arm and shoulder.
Hold this position and return to the start position and repeat to the other side.

Back stretch

Stand with your legs at hip width apart and straight.
Place your hands on your hips.
Lean your body backwards, trying to arch in the lower back as much as you can, lifting your chest up towards the ceiling.
Try to avoid allowing your hips to swing forwards too far.
Hold this position before returning to the start position

Side stretch

Stand with your feet shoulder width apart and place one hand on your hip.
Extend the other hand into the air, leaning over to the side while you increase the stretch by pushing your hips in the opposite direction.
Hold this position before you repeat on the other side. 

Chest opener

Start in a standing position.
Move your arms behind you and interlock your fingers and move your arms slowly upwards.
As you lift your arms upwards you will feel a stretch in your chest and shoulders.
Hold this position, then breathe out and relax.

Side neck stretch

Place one hand behind you in the curve of your lower back, and the other by your side.
Now, bend your neck so that your ear comes closer to the shoulder that is opposite to the arm behind your back.
Hold this position for 30-60 seconds.

Trunk rotations


Stand up straight with your feet shoulder width apart.
Place your hands together and stretch your arms out straight in front of you.
Keeping your hips pointing forwards, rotate your arms from one side and then to the other.
Your feet should remain on the floor throughout the exercise.
Try to feel the rotation coming from your mid to upper body.

Still having pain?

If you are still experiencing pain and discomfort it is recommended to consult a Physiotherapist.

A physiotherapist will assess your cause of pain and provide you with a comprehensive treatment that is correct for you. 

CONNECTING WITH OUR CLIENTS THROUGH TELEHEALTH

What is Telehealth?

 The Health Resources Services Administration defines telehealth as “the use of electronic information and telecommunications technologies to support long-distance clinical health care, patient and professional health-related education, public health and health administration. Technologies include videoconferencing, the internet, store-and-forward imaging, streaming media, and terrestrial and wireless communications”.

Here at Physio Fusion, we will be conducting video consultations for existing and new clients. You will see the same, experienced staff as you would on site at either our New Windsor Branch. With the exception of the hands on aspects, we strive to continue to provide you with the same level of education, advice and exercise progression as you would receive in person.

Telehealth Benefits for Patients:

  • Better access to services for residents/ workers in remote areas (Al-Shorbaji 2013, Bourne et al 2017, Cooper & Allen 2017, Nelson et al 2017) found that this can improve access to care services for clients in isolated areas and virtual consults can address access barriers for patients living in rural locales.
  • More convenient access to services (people avoid the travel and scheduling challenges of attending face-to-face appointments and can access some services after-hours).
  • The ability for patients to ask quick questions without having to book a full consultation
  • Access to high-quality online resources, including videos and digital tools

Telehealth benefits for Physiotherapists:

  • Access to an untapped pool of clinical resources: (Hunt et al 2014): Virtual health programmes offer benefits to clinicians who are looking for increased flexibility in their working life (e.g. semi-retired clinicians or those seeking an improved work/life balance). If offered, this may enable healthcare providers to attract and retain a high-quality workforce, improve staff satisfaction, and access highly specialized resources to improve quality of care.

What is Physitrack and how does it work?

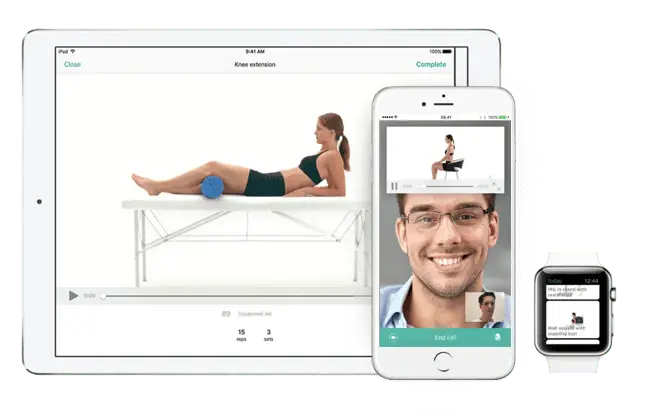
Physitrack is an exercise prescription platform that lets you prescribe home exercises to our clients. It is a program that you as a customer can download for free on your smartphone, tablet or open it with your computer. The videos show how you can perform an exercise correctly and clearly. There are also more than 90 standard exercise protocols and videos with clear explanations about specific complaints or conditions.


How does it work?

Together we determine which exercises are most suitable for you and add these to your program. You will then receive an email with the link to download the Physitrack / app and the link to the program online. Your personal login code is also stated in the same email. If you have downloaded the Physitrack or clicked on the link and enter your password, you can enter your preferences in the program, such as setting reminders. Then you can start with the exercises in a correct and clear manner and contribute to your own recovery!

The attached document is designed to help you prepare for your Telehealth call. PhysiApp_Telehealth_call

What will happen once my appointment is booked?

  • Your Physiotherapist will send an email with more details on how the consultation will take place.
  • Before your appointment you will receive another email from Physitrack with a link to where the consultation will take place.
  • Make sure that you have a working camera and microphone.
  • Make sure you’re using a modern browser, such as Chrome, Firefox, Safari or Microsoft Edge.
  • If you are using a mobile device for your consultation, you will be prompted to download Physitrack app Please do this and then click join as a guest.
  • We ask that you get online 10 minutes before your appointment and click on a link to join the consultation.
  • If you are using a computer, make sure your camera and microphone are available and enabled.
  • Please ensure that you have enough space in case you are required too perform exercises.

What happens if internet is interrupted or my technology fails during the consultation?

If we can call you, we will attempt to continue and complete the consultation via face time.

Here’s how to book your first Telehealth Consultation with us

Save time and book your appointments online with Physio Fusion 24 hours a day, 7 days a week. You can book your appointments via phone or online